3 CEUs
As therapists, we have an extensive list of protocols to return our athletes to play, but the biggest determining factor to get them back on the field or court is pain. Even if all the tests indicate that they are ready, they won’t be able to play if they report pain when executing certain movements required in their sport.
load more
3 CEUs
In many cases in sport and exercise medicine, physical assessment is aimed at establishing a structural diagnosis to guide an effective treatment plan in the hope that someone will fully recover. The expert clinician appreciates pain as a protective output, maintains a level of vigilance for when it is necessary to take a broader approach, assesses the various contributors to the patient's pain and considers secondary factors that may act to modulate it at the peripheral and/or central levels.
This approach, which incorporates advances in pain science, will mean fewer patients are given inappropriate treatment that is missing an important element of their condition.
load more

3 CEUs
-
that pain does not provide a measure of the state of the tissues;
-
that pain is modulated by many factors from across somatic, psychological and social domains;
-
that the relationship between pain and the state of the tissues becomes less predictable as pain persists; and
-
that pain can be conceptualised as a conscious correlate of the implicit perception that tissue is in danger. These issues raise conceptual and clinical implications, which are discussed with particular relevance to persistent pain.
This paper argues that the biology of pain is never really straightforward, even when it appears to be. It is proposed that understanding what is currently known about the biology of pain requires a reconceptualisation of what pain actually is, and how it serves our livelihood.
There are four key points:
Finally, this conceptualisation is used as a framework for one approach to understanding complex regional pain syndrome.
load more

3 CEUs
Chronic musculoskeletal pain (CMP) refers to ongoing pain felt in the bones, joints and tissues of the body that persists longer than 3 months. For these conditions, it is widely accepted that secondary pathologies or the consequences of persistent pain, including fear of movement, pain catastrophizing, anxiety and nervous system sensitization appear to be the main contributors to pain and disability.
While exercise is a primary treatment modality for CMP, the intent is often to improve physical function with less attention to secondary pathologies. Exercise interventions for CMP which address secondary pathologies align with contemporary pain rehabilitation practices and have greater potential to improve patient outcomes above exercise alone.
Biopsychosocial treatment which acknowledges and addresses the biological, psychological and social contributions to pain and disability is currently seen as the most efficacious approach to chronic pain. This clinical update discusses key aspects of a biopsychosocial approach concerning exercise prescription for CMP and considers both patient needs and clinician competencies.
load more

3 CEUs
Pages 5 - 16.
This section discusses the mechanisms of pain. Without being too technical and whilst not relevant to every patient, it gives good insight into nociception, the processing of nociception and the production of pain. Issues such as the modulation of pain, both habituation (turning down) and sensitization (amplification) are discussed. A basic and brief section for any patient who might want to further details about pain mechanisms is provided.
Each page can be printed separately and used as an infographic.
load more

3 CEUs
Pages 17 - 28.
The backbone of this workbook might be the most important section. Key messages are ideally delivered at the right time to the right person. They help patients reconceptualize pain, change their beliefs about pain and facilitate healthy behaviours to help with pain.
This section could be printed in its entirety, or any individual page could be printed on each patient visit and viewed as a standalone infographic.
load more
3 CEUs
Pages 29 - 46.
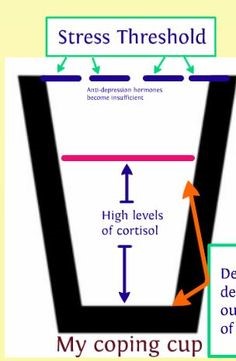
Pain is multidimensional and influenced by a number of factors besides tissue damage. This section overlaps with the Key Messages and starts to give the reader more information about potential contributors to pain. You can also view it a little like a myth debunker. We have information on posture, strength, movement habits, sitting, mechanical deformities, depression, fear and exercise. Again, each page can be used as an infographic.?
You can print parts of this section or have your patient read the whole thing.
load more

3 CEUs
Pages 47 - 71.
Pain is multidimensional and influenced by a number of factors besides tissue damage. This section overlaps with the Key Messages and starts to give the reader more information about potential contributors to pain. You can also view it a little like a myth debunker. We have information on posture, strength, movement habits, sitting, mechanical deformities, depression, fear and exercise. Again, each page can be used as an infographic.
You can print parts of this section or have your patient read the whole thing.
load more